Pregnancy can feel normal while blood pressure, blood sugar, anemia, thyroid function or fetal growth changes without obvious symptoms. Knowing when visits happen, what each appointment checks and which warning signs cannot wait helps you follow the right care plan and seek help promptly.
Key takeaways
- Attend visits every four weeks until 28 weeks in an uncomplicated pregnancy.
- Ask when each blood test, ultrasound and screening result is due.
- Call the maternity team the same day for bleeding, fluid loss or severe headache.
- Expect more frequent monitoring when you have diabetes, hypertension or a multiple pregnancy.
How often should you see an obstetrician during pregnancy?
An uncomplicated pregnancy usually follows a planned pregnancy consultation schedule, not appointments only when you feel unwell. A commonly used pattern is:
- Up to 28 weeks: about one visit every four weeks
- 28 to 36 weeks: about one visit every two weeks
- 36 weeks until delivery: about one visit each week
This schedule is risk-dependent. Twins, high blood pressure, diabetes, bleeding, previous pregnancy complications, abnormal test results, or concerns about fetal growth can require earlier reviews, additional scans, or specialist care.
The World Health Organization recommends at least eight antenatal contacts, so your obstetrician and gynecologist may use a schedule that differs from the traditional monthly pattern.
Attend regular prenatal visits even when you feel well because several pregnancy complications begin without noticeable symptoms. A visit can identify raised blood pressure, protein in urine, anemia, gestational diabetes, medication problems, depression, or slower-than-expected fetal growth.
Your clinician can also update vaccinations, review nutrition and folic-acid use, discuss activity and medicines, and answer questions before a small concern becomes urgent.
A normal examination or screening result does not guarantee a complication-free pregnancy. Screening has false-positive and false-negative results, and problems can develop between antenatal contacts. Contact your maternity team promptly if fetal movement becomes less than usual, rather than waiting for the next appointment.
What happens at a routine pregnancy consultation?
A routine visit combines maternal measurements, symptom questions and a fetal check. You may feel well while high blood pressure, anemia, urinary infection or poor fetal growth is developing, so each part has a purpose.
| Check | What the clinician assesses | What an abnormal result may prompt |
|---|---|---|
| Blood pressure during pregnancy | Pressure and trends since the last visit | Repeat measurements, blood tests or urgent assessment for possible preeclampsia |
| Weight checks | Expected change and sudden gain | Review of nutrition, fluid retention or other symptoms |
| Urine testing | Protein, glucose, blood and infection indicators | Further testing or treatment |
| Fundal-height measurement | Uterine growth after about 20 weeks | Ultrasound if growth or fluid levels seem unusual |
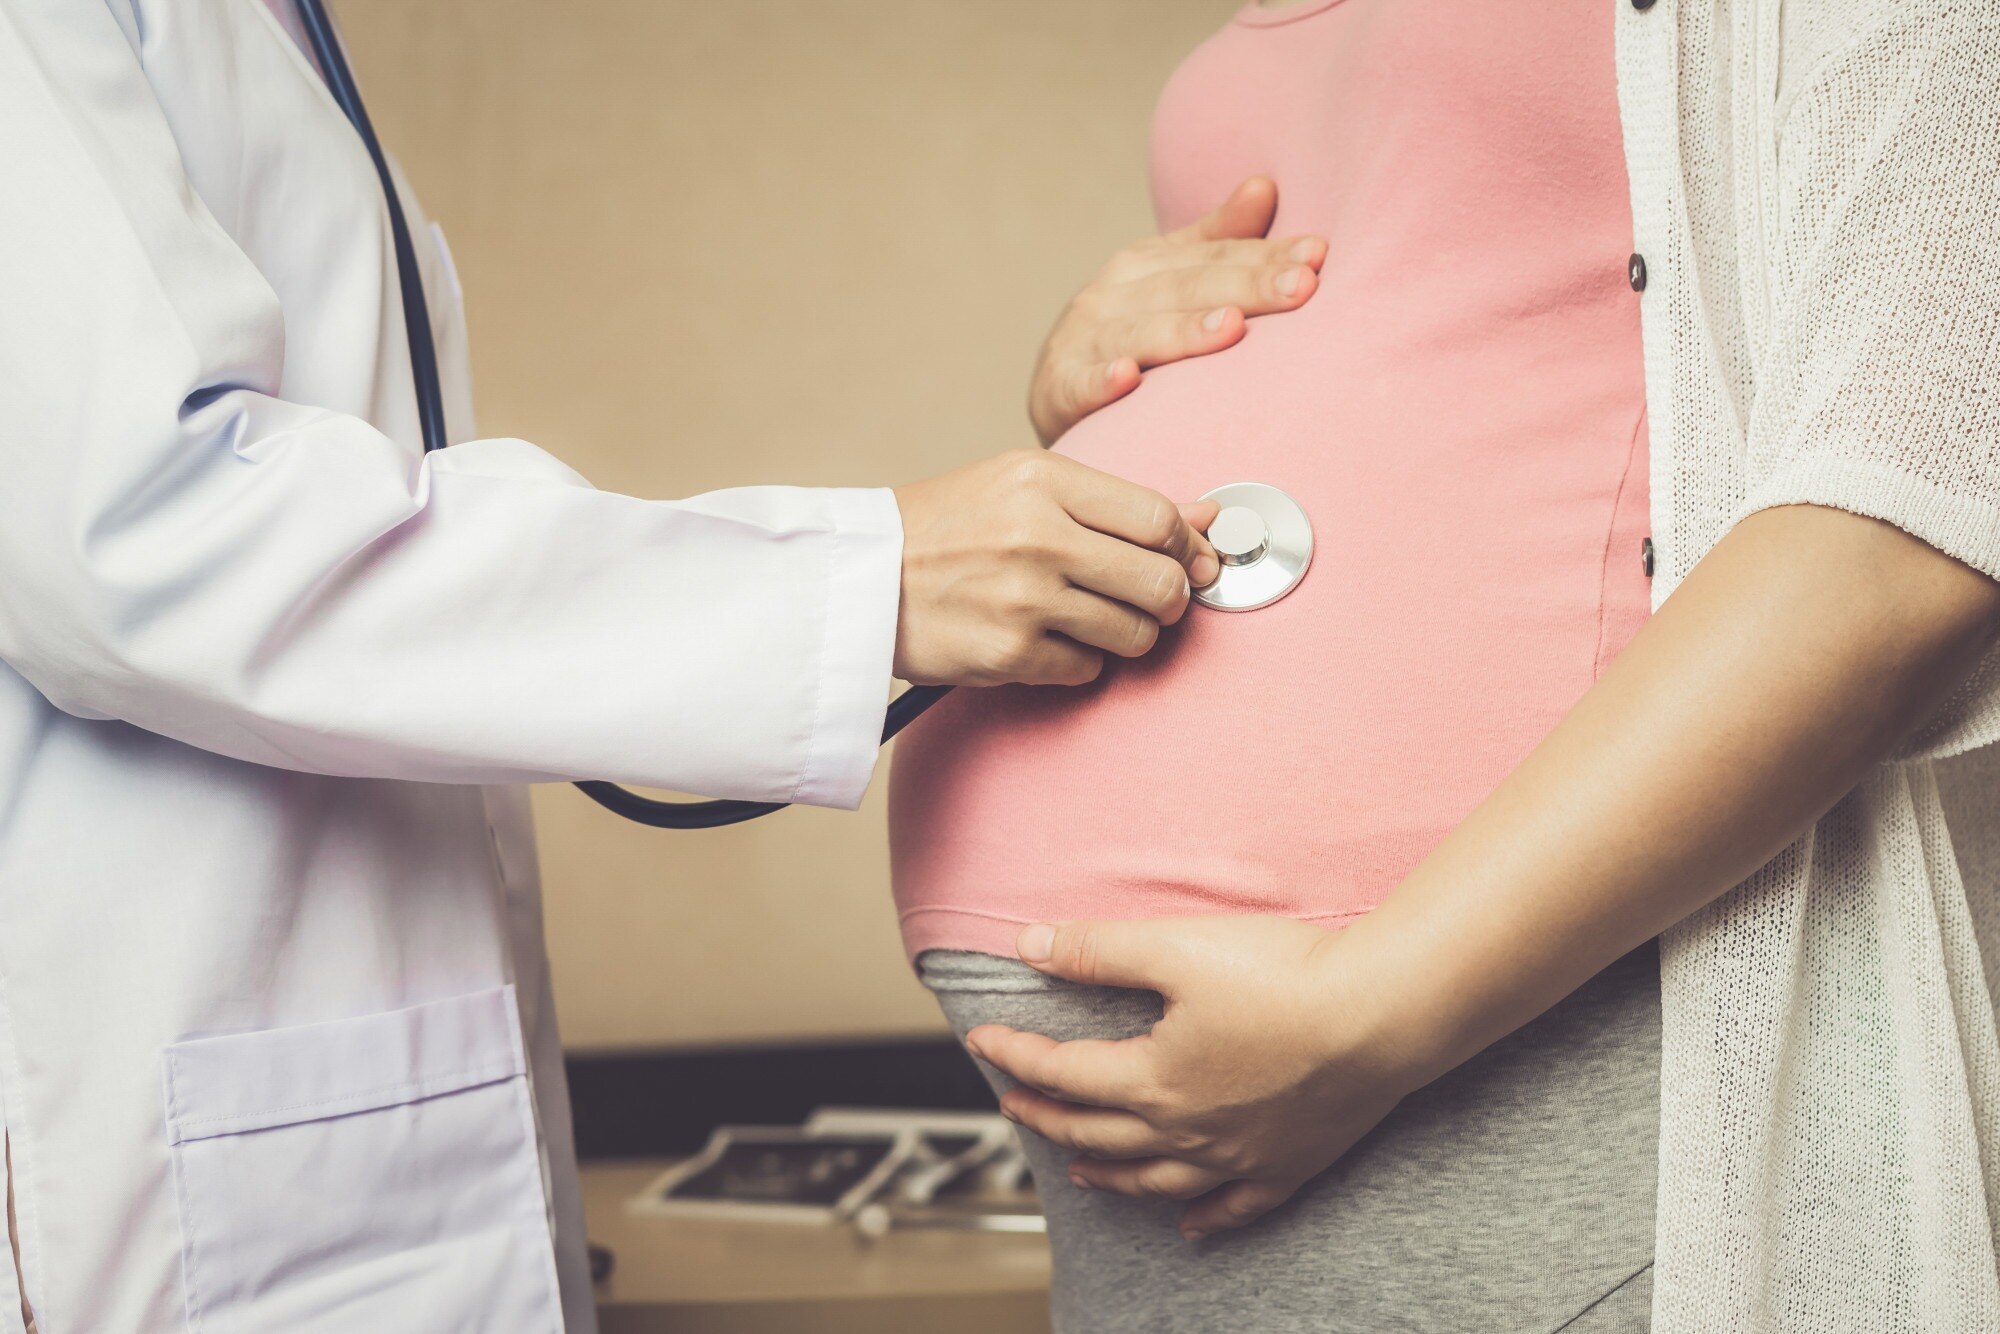
| Fetal heart rate assessment | Heart rate and rhythm with a Doppler or monitor | Immediate or additional fetal surveillance if the rate is concerning |
Your clinician will ask about headache, visual changes, abdominal pain, bleeding, leaking fluid, contractions, breathlessness and fetal movement. Mention vomiting, sleep, mood, medicines, supplements and any new diagnosis; medication doses and mental-health symptoms belong in this review too.
The clinician reviews blood counts, blood group, infection screening and other results, then examines you when indicated. That examination may include swelling, abdominal tenderness, uterine size or a pelvic examination; a pelvic examination is not required at every ordinary visit.
Later in pregnancy, report reduced or changed movement promptly rather than waiting for the next appointment.
Which pregnancy tests and scans are discussed at each stage?
Testing is staged so each result answers a different question. At the first visit, your obstetrician usually discusses blood group and Rh status, a complete blood count for anaemia, HIV, hepatitis B, syphilis, urine testing and a dating ultrasound. The schedule changes if you have diabetes, bleeding, high blood pressure or a previous pregnancy complication.
Screening | Diagnostic testing What it does | Estimates the chance of a condition | Determines whether a specified chromosomal condition is present Common examples | Cell-free DNA screening, serum screening, nuchal translucency screening | Chorionic-villus sampling or amniocentesis Timing | Cell-free DNA from about 10 weeks; nuchal translucency screening at 11–13 weeks and 6 days | Chorionic-villus sampling at about 10–13 weeks; amniocentesis from about 15 weeks Trade-off | No procedure-related miscarriage risk, but false-positive and false-negative results occur | Invasive, with a small procedure-related miscarriage risk, but provides a definitive result for the condition tested
The anomaly scan is usually offered at 18–22 weeks to examine fetal anatomy, growth, placenta and amniotic fluid. Gestational diabetes testing is usually done at 24–28 weeks; it matters even without symptoms because high glucose can affect fetal growth and pregnancy health.
Your clinician may repeat blood counts or infection tests when indicated, then offer Group B Streptococcus screening at 36–37 weeks. A normal scan or screening result cannot rule out every complication, so attend follow-up and report concerning symptoms promptly.
Which symptoms need a same-day call or urgent assessment?
Call your obstetrician or maternity unit the same day for pregnancy warning signs rather than waiting for your next appointment. Go to hospital immediately for heavy bleeding, severe pain, fainting, chest pain, serious breathing difficulty, or symptoms that feel life-threatening.
| Symptom | Action | Why it matters |
|---|---|---|
| Vaginal bleeding, especially heavy bleeding, clots, pain or dizziness | Call immediately; attend hospital for heavy bleeding or severe symptoms | It can signal placental or pregnancy complications |
| Leaking fluid from the vagina | Contact your maternity unit promptly, even without contractions | The membranes may have ruptured, increasing infection and preterm-birth risks |
| Reduced fetal movement after you have established a usual pattern | Call promptly; do not wait until the next day | Assessment of the fetal heart rate may be needed |
| Severe headache, blurred vision or flashing lights, upper-abdominal pain, sudden face or hand swelling | Seek urgent assessment | These can indicate preeclampsia, which can develop after 20 weeks |
| Chest pain, breathlessness at rest, fainting or one-sided leg swelling and pain | Attend emergency care immediately | These symptoms can indicate a serious heart, lung or clotting problem |
| Regular painful contractions before 37 weeks or strong pelvic pressure with backache | Call the maternity unit the same day | These may indicate preterm labour |
A normal scan or recent normal visit does not rule out a problem developing afterward. If you cannot reach your obstetrician, use the hospital’s labour-and-delivery or emergency department rather than delaying care.
How does your care plan change when pregnancy needs closer monitoring?
More frequent visits are needed when a condition raises the risk of hypertension, poor fetal growth, preterm birth, or delivery complications. Your obstetrician may add blood tests, growth scans, fetal monitoring, or a maternal-fetal-medicine consultation rather than simply moving every appointment closer together.
| Condition | What may change | Records to bring |
|---|---|---|
| Pre-existing hypertension, diabetes, kidney or autoimmune disease | Earlier review, medication assessment, extra blood-pressure, urine, blood and growth checks | Diagnosis notes, medicine list, recent laboratory and scan reports |
| Previous preeclampsia or preterm birth | Closer blood-pressure and cervical or fetal-growth surveillance, with a documented prevention plan | Prior discharge summary, delivery date, complications and treatment records |
| Twins pregnancy or suspected growth problem | More frequent ultrasounds and fetal surveillance; delivery timing may change | All ultrasound reports, including measurements and dates |
| Previous cesarean birth or abnormal placental findings | Placental-location review and a planned discussion of vaginal birth after cesarean or repeat cesarean | Operative note, previous discharge summary and scar-related records |
| IVF pregnancy care | Review of embryo-transfer details, medications and early scans, followed by risk-based surveillance | Fertility-clinic summary, transfer date, embryo details and prescriptions |
Bring your blood-pressure log, glucose readings, vaccination record, medication list, scan reports and questions to every review. Do not stop aspirin, insulin, thyroid medicine or fertility medication without advice.
A Pune maternity team can coordinate appointments by sharing one updated record with the obstetrician, fertility specialist, radiologist and physician managing an existing disease. Deshmukh Maternity Hospital can use that shared plan to schedule scans, specialist reviews and delivery discussions without making you repeat the same history at each visit.
Related service
Gynecological Consultations & Treatments Gynecological Consultations & Treatments Comprehensive Care for Every Stage of Womanhood At Deshmukh Maternity Hospital, we are dedicated to providing expert gynecological care tailored to... View service → |
Frequently asked questions
How often should you see an obstetrician during pregnancy?
A commonly used schedule is every four weeks until 28 weeks, every two weeks from 28 to 36 weeks, and weekly from 36 weeks until birth. Your obstetrician may change this plan for twins, hypertension, diabetes, previous pregnancy complications or abnormal test results.
What happens at a routine pregnancy consultation?
The consultation usually includes a review of symptoms, medicines and test results; blood pressure and weight checks; measurement of the uterus after it becomes useful; discussion of fetal movement later in pregnancy; and planning for the next tests or scan.
Which tests and scans are discussed during pregnancy?
Early care commonly covers blood group and Rh status, haemoglobin, urine testing, infection screening and dating ultrasound. The 11- to 13-week period may include first-trimester screening, the 18- to 22-week period commonly includes the anatomy scan, and later testing depends on your health, symptoms and fetal growth.
Which pregnancy symptoms need a same-day call or urgent assessment?
Contact your maternity team the same day for vaginal bleeding, suspected fluid loss, painful regular contractions, reduced fetal movement, persistent vomiting, fever, painful urination, severe headache or visual changes. Seek urgent assessment for heavy bleeding, severe abdominal pain, fainting, seizures, chest pain or difficulty breathing.
How does care change when a pregnancy needs closer monitoring?
Your care team may shorten the interval between visits, repeat blood or urine tests, arrange growth ultrasounds, check blood pressure more frequently, or add fetal monitoring such as a nonstress test. The plan depends on the condition and the results, not on a fixed schedule for every pregnancy.