IUI is not suitable for every fertility problem: it places prepared sperm in the uterus, but fertilization still normally depends on an open fallopian tube and ovulation. By the end, you will know whether the treatment may fit your diagnosis, what testing and scheduling it involves, and what to ask before starting a cycle.
Key takeaways
- IUI may suit unexplained infertility, ovulation problems, donor sperm, or ejaculation difficulties.
- Confirm ovulation, semen quality, fallopian-tube patency, and infection screening before IUI.
- Timing insemination around ovulation is central to each IUI cycle.
- Seek urgent care for severe pain, heavy bleeding, breathing trouble, or rapid abdominal swelling.
Who May Benefit From IUI—and When It Is a Poor Fit
Who may benefit from IUI includes people with unexplained infertility, ovulation disorders, cervical-factor infertility, ejaculation or erectile difficulties, and those using donor sperm. It can also suit single women and female couples trying to conceive without a male partner.
For unexplained infertility, clinicians often pair IUI with letrozole or clomiphene for a limited number of cycles before considering IVF. Injectable gonadotropins require close monitoring because several follicles can lead to a multiple pregnancy.
- Completely blocked or severely damaged fallopian tubes: IUI cannot carry sperm past an obstruction. Tubal surgery or IVF may be more appropriate.
- Severe male-factor infertility: Very low sperm production, count, or motility can leave too few usable sperm after laboratory preparation; IVF with intracytoplasmic sperm injection may be needed.
- Severe endometriosis: Pelvic damage and reduced fertility can make IVF a better option.
- Diminished ovarian reserve, advanced reproductive age, or previous unsuccessful treatment: Limited time or egg supply can favour moving directly to IVF.
- Untreated pelvic infection: Treat the infection before insemination.
| Situation | Why IUI may fit | When to reconsider |
|---|---|---|
| Unexplained infertility | Sperm is placed closer to the egg during the fertile window | Move to IVF after the agreed limited trial |
| Ovulation disorder | Medication can produce predictable ovulation | Reassess if follicles do not develop or too many develop |
| Cervical-factor infertility | The catheter bypasses cervical mucus | Investigate other causes if cycles fail |
Before choosing IUI, confirm ovulation, semen quality, at least one open tube with a test such as hysterosalpingography, and the absence of untreated infection.
The Tests, Medicines and Timing Used Before IUI
A blocked fallopian tube or sperm problem beyond laboratory preparation can make IUI a poor choice, so clinicians test before prescribing medication. The IUI tests usually examine ovulation, sperm, egg supply and whether sperm can reach the egg.
- Semen analysis measures sperm count, movement and shape. The result helps determine whether prepared sperm are likely to provide a reasonable chance.
- Ovulation assessment uses cycle history, LH urine testing, blood progesterone or ultrasound. It shows whether and when an egg is being released.
- Ovarian reserve testing uses antral follicle count, anti-Müllerian hormone and sometimes follicle-stimulating hormone. It helps set expectations and choose treatment intensity; it does not predict IUI success by itself.
- Tubal-patency testing, commonly hysterosalpingography, checks whether at least one fallopian tube is open. Clinicians also address untreated pelvic infection before proceeding.
The cycle plan depends on ovulation, age, test results, previous treatment and the risk of multiple pregnancy.
| Option | What it involves | When it applies |
|---|---|---|
| Natural cycle | Monitoring your own follicle and timing IUI around ovulation | Regular ovulation with suitable sperm and an open tube |
| Oral medication | Letrozole or clomiphene encourages follicle development, followed by monitoring | Irregular ovulation or unexplained infertility |
| Injectable gonadotropins | Injections stimulate several follicles under close ultrasound monitoring | Selected cases after careful counselling; many clinics restrict this option because multiple pregnancy risk rises |
If too many follicles develop, the clinician may cancel insemination. Stimulation also carries a risk of ovarian hyperstimulation syndrome; severe abdominal swelling, vomiting, breathlessness or reduced urination needs urgent medical advice.
What Happens From the First Cycle-Day Call to Insemination
Your IUI cycle starts with a call on the first day of full menstrual bleeding. The clinic records that date, schedules baseline checks, and confirms whether you will use a natural cycle or medication-assisted stimulation.
1. In a natural cycle, the clinic tracks ovulation with an LH urine test, blood testing, or ultrasound. In a stimulated cycle, ultrasound scans and sometimes blood tests track follicle growth after medication.
2. When a mature follicle is ready, you receive a trigger injection, usually containing hCG. The clinic gives you an exact insemination time, often about 24–36 hours later.
3. You provide a fresh semen sample on the scheduled day. Follow the clinic’s instructions about collection at home or in a private room, transport time, and the container to use.
4. The laboratory performs sperm washing: it removes seminal fluid and debris, selects the more motile sperm, and concentrates them into a small volume. Raw semen is not normally placed directly into the uterus.
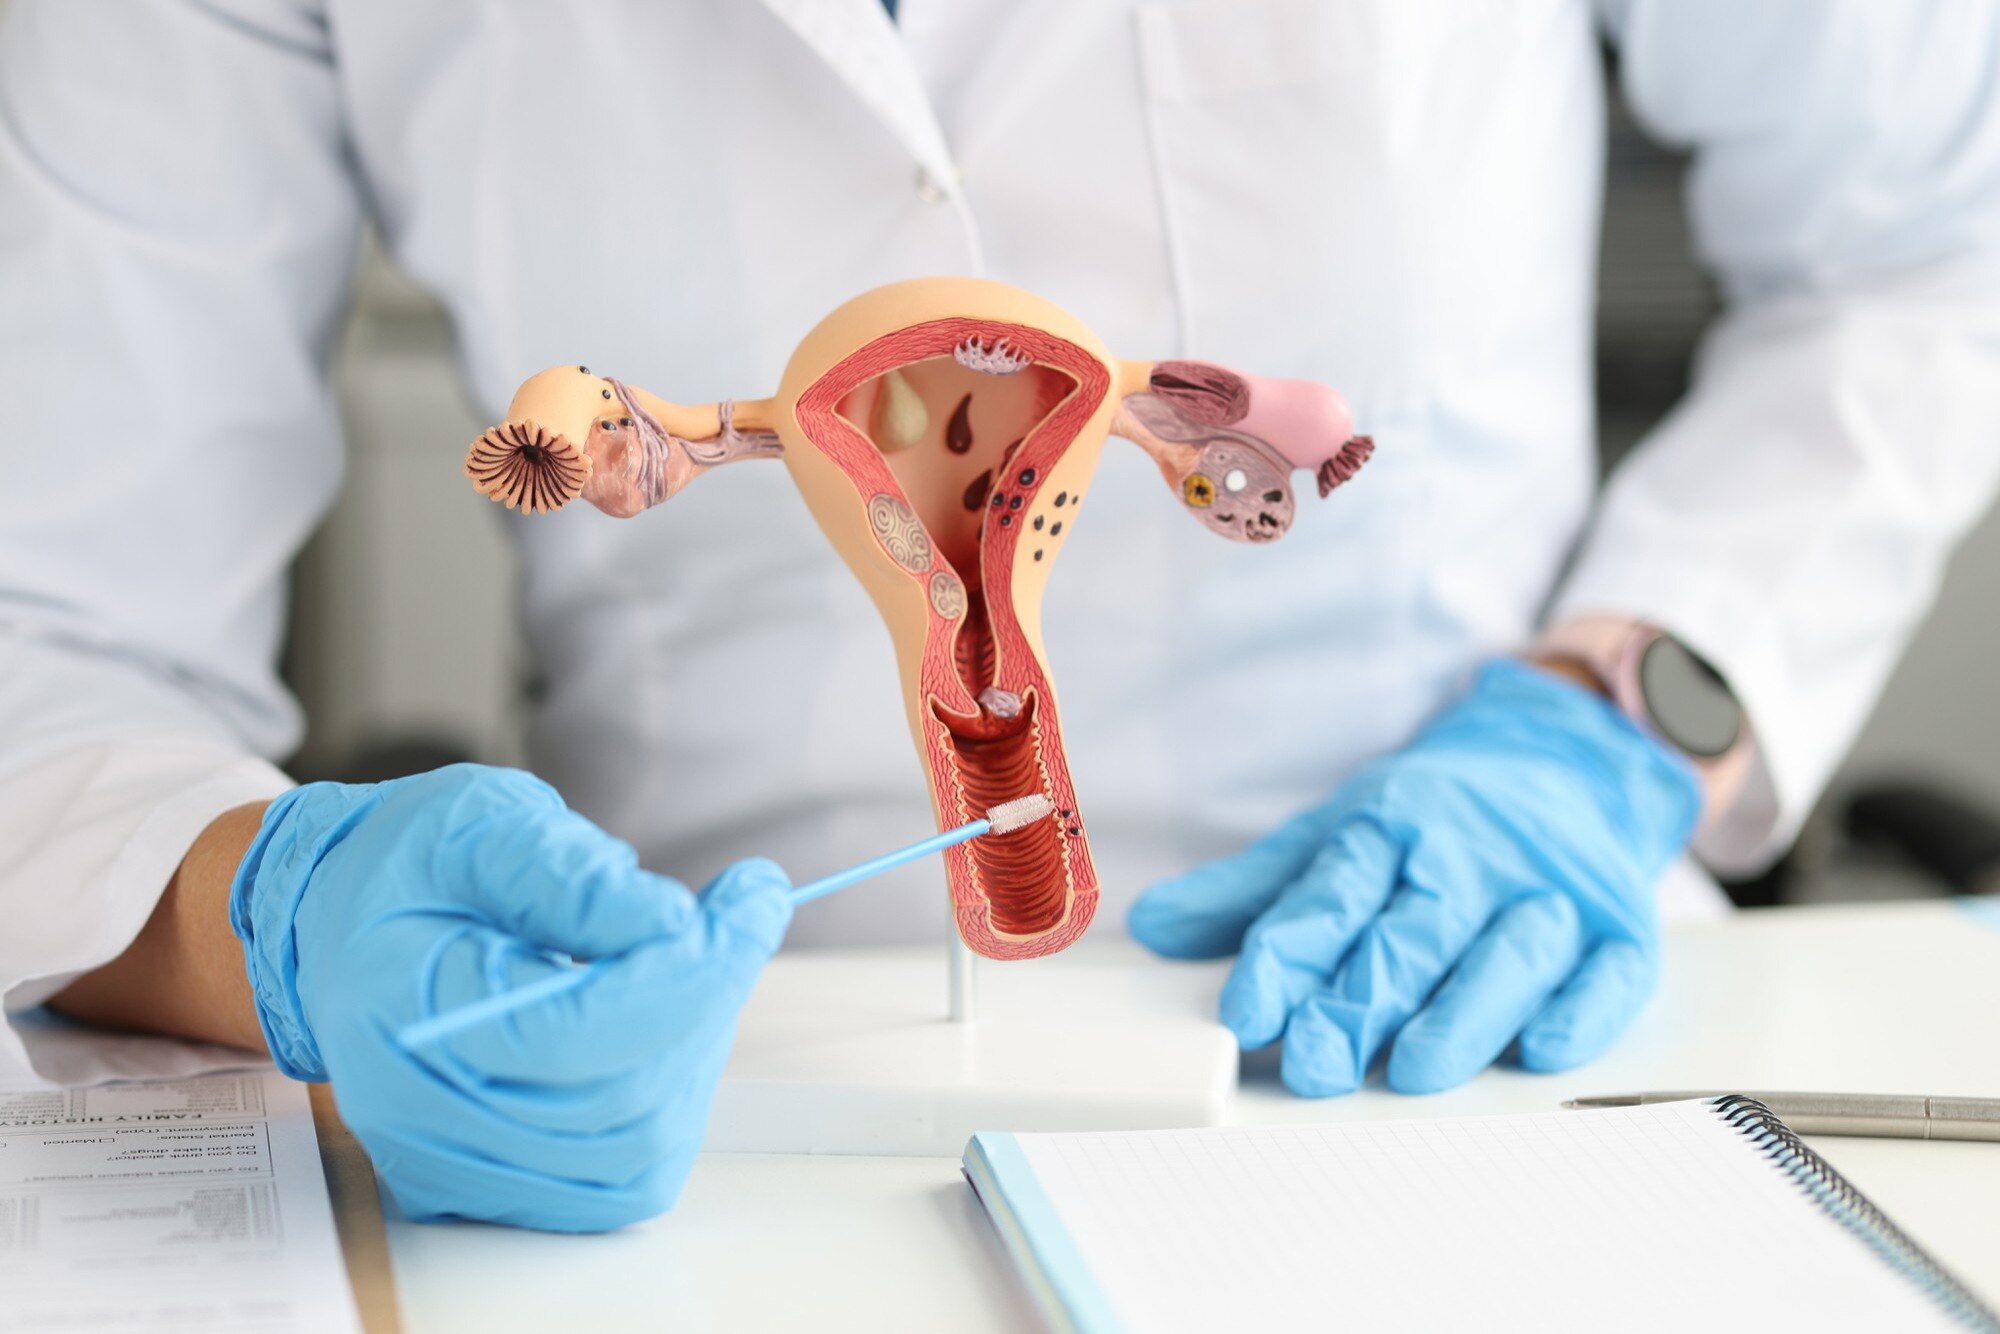
5. For the IUI procedure, you lie on an examination table while the clinician inserts a speculum to see the cervix. A thin catheter passes through the cervix into the uterus and releases the prepared sperm.
6. The insemination itself usually takes only a few minutes and does not require anesthesia. Mild cramping or spotting can occur afterward, but the clinic will tell you which symptoms need prompt advice.
What to Expect After IUI: Results, Risks and Red Flags
After IUI, resume normal activity unless your clinician gives different instructions. Bed rest does not improve implantation. Mild cramping or light spotting can occur; severe pain is not expected. Take prescribed medicines as directed, and ask before taking a new drug.
Wait about 14 days for an IUI pregnancy test. Testing sooner after an hCG trigger injection can detect the medication rather than a pregnancy and give a false-positive result. If the test is negative but your period does not begin, ask when to repeat it before stopping progesterone.
Results are assessed in stages:
| Measure | What it shows | Timing |
|---|---|---|
| IUI pregnancy test | hCG in urine or blood | About 14 days after insemination |
| Ultrasound | Pregnancy location, gestational sac and heartbeat | After a positive test, according to clinic advice |
| IUI success rate | Pregnancies per treatment cycle, not a guarantee for you | Compare only when age, diagnosis and outcome definition match |
Ask whether a quoted IUI success rate means a positive test, clinical pregnancy or live birth. Live birth is the final outcome, while ultrasound also checks for an ectopic pregnancy.
Seek urgent medical advice for marked abdominal swelling or pain, repeated vomiting, breathlessness, fainting, very little urine, heavy bleeding, or one-sided pain with shoulder-tip pain. These symptoms can signal ovarian hyperstimulation syndrome or another emergency. Stimulated IUI also carries a multiple-pregnancy risk, especially when several follicles develop; follow-up ultrasound is important.
How to Compare IUI With IVF and Choose a Treatment Plan
Choose IUI when you want a less invasive, lower-laboratory treatment and at least one fallopian tube is open. Choose IVF when tubal damage, severe sperm impairment, diminished ovarian reserve, age, or previous treatment makes fertilisation outside the body more useful.
| Factor | IUI | IVF |
|---|---|---|
| Invasiveness | Speculum and thin catheter; usually no anaesthesia | Ovarian egg retrieval requires sedation or anaesthesia |
| Medication and monitoring | Natural cycle or letrozole/clomiphene; ultrasound monitoring; injectable drugs raise multiple-pregnancy risk | Injectable stimulation, repeated scans and blood tests; trigger injection before retrieval |
| Laboratory work | Sperm is washed and placed in the uterus; fertilisation occurs in the body | Eggs and sperm meet in a laboratory; embryos are assessed before transfer |
| Cost | Lower initial IUI cost, but repeated cycles add up | Higher single-cycle cost, including retrieval, laboratory work and possible storage |
| Pregnancy risk | Several mature follicles can produce twins or higher-order pregnancy; the clinic may cancel the cycle | Transferring one embryo reduces, but does not eliminate, multiple-pregnancy risk |
| Embryo freezing | No embryos are created for freezing | Suitable embryos can be frozen for later transfer |
Ask these IUI consultation questions:
- What is my estimated chance per cycle, and how many cycles will we try before IVF?
- What follicle number would make you cancel insemination?
- Which medicines, scans, sperm-washing fees and pregnancy tests are included in the IUI cost?
- What donor sperm requirements cover screening, consent, documentation and storage?
- If I choose IVF, will you recommend single-embryo transfer and what are the freezing charges?
Deshmukh Maternity Hospital can help you compare an itemised IUI plan with IVF rather than choosing from a headline procedure price.
Related service
IUI Treatment At Deshmukh Hospital & IVF Center, we provide safe, affordable, and personalized Intrauterine Insemination (IUI) Treatment for couples facing... View service → |
Frequently asked questions
Who may benefit from IUI treatment?
IUI may help with unexplained infertility, ovulation disorders, cervical-factor infertility, ejaculation or erectile difficulties, and donor-sperm conception. It can also support single women and female couples trying to conceive without a male partner.
What tests and medicines are used before IUI?
Assessment can include ovulation tracking, semen analysis, fallopian-tube evaluation, and infection screening. Medicines may stimulate ovulation, followed by monitoring and carefully timed insemination.
What happens during an IUI procedure?
A processed sperm sample is placed through a thin catheter into the uterus around ovulation. The procedure is brief, and you can usually resume routine activities afterward unless your clinician advises otherwise.
What should you expect after IUI?
Mild cramping or light spotting can occur. Take a pregnancy test when your clinic advises, and seek medical care for severe pain, heavy bleeding, breathing difficulty, or rapid abdominal swelling.
How does IUI compare with IVF?
IUI is less invasive and usually involves fewer procedures, while IVF fertilizes eggs outside the body and offers more control over fertilization and embryo transfer. Your diagnosis, age, ovarian reserve, sperm results, tubal status, and previous treatment determine the better plan.